Резюме
Определение
Анамнез и осмотр
Ключевые диагностические факторы
- início agudo de pele vermelha, dolorida, quente e inchada (celulite)
- pele elevada, bem demarcada e vermelha viva (erisipela)
Другие диагностические факторы
- aparência de casca de laranja
- formação de vesículas
- sangramento
- Linfangite
- unilateralidade
- febre
- mal-estar
- linfadenopatia
- anormalidades no espaço entre os pododáctilos
- fatores de risco
- outros sintomas constitucionais
- fonte de infecção
- fatores imunocomprometedores
- viagem recente
- flutuação profunda na celulite
- necrose dérmica
- sinais de sepse
- sinais de fasciite necrosante
- sinais de celulite orbitária ou periorbitária
Факторы риска
- diabetes
- edema crônico e insuficiência venosa
- eczema
- linfedema
- episódios prévios de celulite
- anormalidades no espaço entre os pododáctilos
- uso de substâncias por via intravenosa
- obesidade
Диагностические исследования
Исследования, которые показаны в первую очередь
- hemograma completo
- velocidade de hemossedimentação (VHS)
- proteína C-reativa
- ureia e eletrólitos
- hemocultura e sensibilidades
Исследования, проведение которых нужно рассмотреть
- Zaragatoa de pele
- aspirado de pele
- biópsia de pele
- procedimentos de diagnóstico molecular
- Ultrassonografia no local de atendimento (POCUS)
- radiografia simples
- RNM
- ultrassonografia
- testes da função hepática
Алгоритм лечения
suspeita de sepse
grave: qualquer sítio (exceto perto dos olhos ou nariz)
qualquer gravidade: local próximo aos olhos ou nariz
não grave: qualquer local (exceto perto dos olhos ou nariz)
recidivas frequentes
Составители
Эксперты-консультанты
Alexander Alexiou, MBBS, BSc, DCH, FRCEM, Dip IMC RCSEd
Emergency Medicine Consultant
Barts Health NHS Trust
Physician Response Unit Consultant
London’s Air Ambulance
Royal London Hospital
UK
Раскрытие информации
AA declares that he has no competing interests.
Jamie Scott, MB BCh, BAO, MSc, FRCEM
Emergency Medicine Consultant
Newham Hospital
Barts Health NHS Trust
Physician Response Unit Senior Fellow
London’s Air Ambulance
Royal London Hospital
Flight Doctor
Essex and Herts Air Ambulance Trust
UK
Disclosures
JS declares that he has no competing interests.
Ram Narayanan, MBBS, MEM, MRCEM
ST5 in Emergency Medicine
Whipps Cross Hospital
Barts Health NHS Trust
London
UK
Disclosures
RN declares that he has no competing interests.
Acknowledgements
BMJ Best Practice would like to gratefully acknowledge previous expert contributors to this topic, whose work has been retained in parts of the content:
Matthew C. Robinson, MD
Infectious Disease Physician
Austin Infectious Disease Consultants
Austin
TX
Disclosures: MCR declares that he has no competing interests.
Johann Grundlingh MBChB, FCEM, FFICM, EDICM, DFMS, DipMedTox, MMedTox, MSB, ERT, MEWI, MBA
Emergency Medicine Consultant
Royal London Hospital
Barts Health NHS Trust
Honorary Senior Lecturer
Queen Mary University
London
UK
Disclosures: JG declares that he has no competing interests.
Peer reviewers
Susan Croft, MBChB, MRCP, FRCEM
Emergency Medicine Consultant
Sheffield Teaching Hospitals NHS Foundation Trust
Sheffield
UK
Disclosures
SC declares that she delivered two paid presentations to local general practitioners on acute exacerbations of long-term conditions in March and April 2018 (supported by Astra-Zeneca).
Peer reviewer acknowledgements
BMJ Best Practice topics are updated on a rolling basis in line with developments in evidence and guidance. The peer reviewers listed here have reviewed the content at least once during the history of the topic.
Disclosures
Peer reviewer affiliations and disclosures pertain to the time of the review.
References
Key articles
Sartelli M, Coccolini F, Kluger Y, et al. WSES/GAIS/WSIS/SIS-E/AAST global clinical pathways for patients with skin and soft tissue infections. World J Emerg Surg. 2022 Jan 15;17(1):3.Full text Abstract
Stevens DL, Bisno AL, Chambers HF, et al. Practice guidelines for the diagnosis and management of skin and soft tissue infections: 2014 update by the Infectious Diseases Society of America. Clin Infect Dis. 2014 Jul 15;59(2):e10-52.Full text Abstract
National Institute for Health and Care Excellence. Cellulitis and erysipelas: antimicrobial prescribing. Sep 2019 [internet publication].Full text
Reference articles
A full list of sources referenced in this topic is available to users with access to all of BMJ Best Practice.
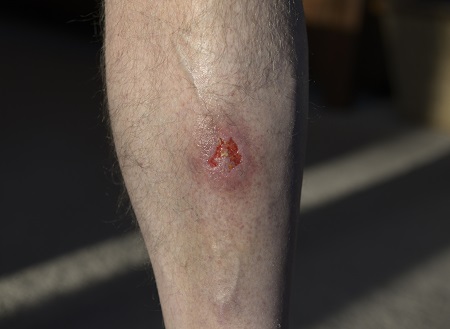
Differentials
- Fasciite necrosante
- Superficial, tromboflebite
- Trombose venosa profunda
More DifferentialsGuidelines
- Guidelines on the management of cellulitis in lymphoedema
- WSES/GAIS/WSIS/SIS-E/AAST global clinical pathways for patients with skin and soft tissue infections
More GuidelinesPatient information
Celulite e erisipela
More Patient information Log in or subscribe to access all of BMJ Best Practice
Use of this content is subject to our disclaimer